Key Takeaways
Hairy cell leukemia is a rare, slow-growing B-cell blood cancer in which abnormal lymphocytes with fine surface projections build up in the bone marrow, spleen, and liver, often causing pancytopenia (a drop in red cells, white cells, and platelets).
- Epidemiology ▾: Hairy cell leukemia mostly affects middle-aged and older men, with a male-to-female ratio of about 4:1, and accounts for roughly 2% of adult leukemias.
- Pathogenesis ▾: Nearly all classic cases carry the BRAF V600E mutation, which switches on a growth-signaling pathway and drives the disease [3].
- Clinical Features ▾: Fatigue, weakness, infections, splenomegaly, and hepatomegaly.
- Laboratory Findings ▾: Diagnosis rests on the blood smear, bone marrow biopsy, flow cytometry (CD19, CD20, CD22, CD11c, CD25, CD103, FMC7), and Annexin A1 staining; very low monocyte counts are a useful clue.
- Treatment ▾: Treatment is given only when patients are symptomatic. First-line therapy is a purine analog (cladribine or pentostatin), increasingly combined with rituximab [2].
- Prognosis ▾: The outlook today is excellent, with 5-year survival around 95% and many patients achieving long, durable remissions [2,4].
*Click on ▾ for more information
Introduction
Hairy cell leukemia is a rare chronic B-cell cancer. The leukemic cells are mature B lymphocytes covered in fine, hair-like projections that give the disease its name. These cells settle into the bone marrow, spleen, and liver, where they crowd out normal blood production. The result is pancytopenia (a drop in red cells, white cells, and platelets) and the symptoms that follow it.
This guide walks you through what causes hairy cell leukemia, how clinicians spot it, and how treatment has changed in the last few decades. The story is genuinely encouraging: a disease that was once fatal within a few years is now one most patients live with for a long time.
Historical Perspective
The disease was first clearly described in 1958 by Bertha Bouroncle and colleagues at Ohio State University. They called it leukemic reticuloendotheliosis [6]. The now-familiar name "hairy cell leukemia" was coined later, by Schreck and Donnelly in 1966, after they noticed the cells' frayed, hair-like surface under the microscope. Major turning points followed: interferon-alpha in the 1980s, the purine analogs (pentostatin and cladribine) shortly after, the discovery of the BRAF V600E mutation in 2011 [3], and the rise of targeted therapy in the years since [1].
Epidemiology
Hairy cell leukemia is uncommon. It makes up fewer than 2% of all adult leukemias, with roughly 1,000 new cases each year in the United States.
A few patterns are remarkably consistent:
- Age: Most patients are middle-aged or older, with peak incidence in the sixth and seventh decades of life.
- Gender: Men are affected far more often than women, at about a 4:1 ratio.
- Geography: The disease occurs worldwide, with some variation between populations that is not yet fully explained.
The cause is unknown. Genetic susceptibility and environmental exposures have been suggested, but no single risk factor has been firmly established.
Pathogenesis
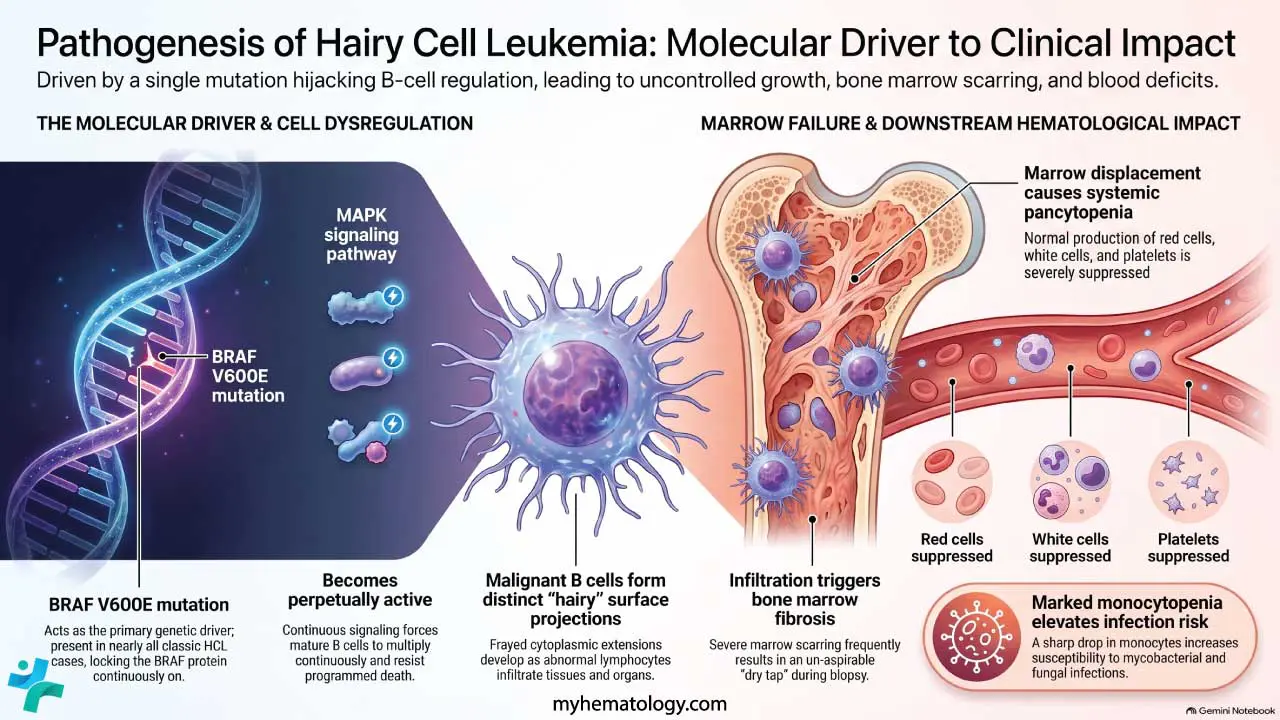
B cells normally develop in the bone marrow, mature in the lymphoid tissues, and differentiate into plasma cells that make antibodies. In hairy cell leukemia, this orderly process is hijacked.
The role of the BRAF V600E mutation
The central driver is the BRAF V600E mutation, found in nearly every case of classic hairy cell leukemia [3]. It locks the BRAF protein into an "always on" state, switching on the MAPK signaling pathway. This pathway tells cells to grow, divide, and resist apoptosis (programmed cell death). The result is a clone of B cells that keeps multiplying when it should be slowing down [1,3].
Why blood counts drop
Hairy cells push out normal blood-forming cells in the marrow. They also encourage bone marrow fibrosis which is a scarring that further reduces healthy hematopoiesis. This is why the bone marrow in hairy cell leukemia often gives a "dry tap": the marrow is too fibrous to aspirate liquid from, so a core biopsy becomes essential.
Two practical consequences follow:
- Pancytopenia explains the fatigue, infections, and bleeding patients describe.
- Monocytopenia (a striking drop in monocytes) is one of the most distinctive findings in hairy cell leukemia and partly explains why patients are vulnerable to mycobacterial, fungal, and Pneumocystis infections [1,2].
Clinical Features
The onset of hairy cell leukemia is usually slow and quiet. Symptoms creep in rather than crashing down, which is why some patients are diagnosed after a routine blood test rather than because of acute illness.
Typical presenting features include:
- Fatigue and weakness from anemia.
- Infections, sometimes unusual or recurrent, due to low neutrophil and monocyte counts.
- Easy bruising and bleeding from low platelets.
- Abdominal fullness or discomfort from splenomegaly.
- Weight loss, fevers, and night sweats in some patients, similar to other lymphoproliferative disorders.
On examination, splenomegaly is the hallmark physical finding and may be massive. Hepatomegaly is less common. Lymphadenopathy is rare. This is an important point that helps distinguish hairy cell leukemia from chronic lymphocytic leukemia and most lymphomas [1].
Laboratory Investigations
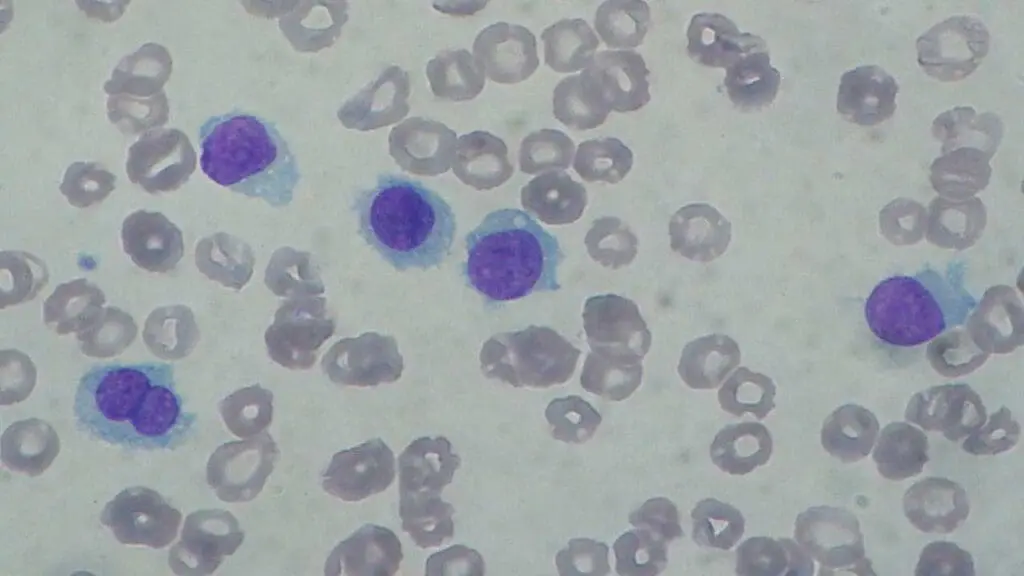
Diagnosis comes together from several lines of evidence: the blood film, the bone marrow biopsy, and the immunophenotype.
Complete blood count
The CBC in hairy cell leukemia typically shows:
- Pancytopenia — anemia, leukopenia, and thrombocytopenia.
- Monocytopenia — a striking and characteristic drop in monocytes.
- Elevated lactate dehydrogenase (LDH) from increased cell turnover.
Peripheral blood smear
The smear may show the hairy cells themselves — mature lymphocytes with fine cytoplasmic projections radiating from the surface. Pancytopenia is also visible on the film.
Bone marrow biopsy
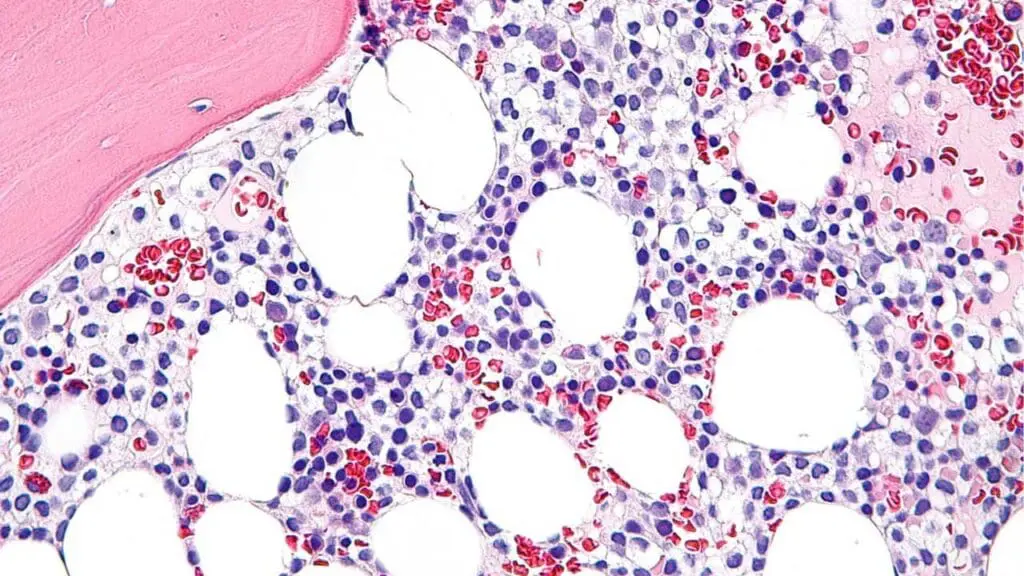
Bone marrow biopsy is essential and often shows a "dry tap" on aspiration because of fibrosis. The biopsy reveals a diffuse infiltrate of small lymphoid cells with abundant clear cytoplasm and oval or indented nuclei — the classic "fried egg" appearance.
Flow cytometry and immunohistochemistry
Hairy cells typically express CD19, CD20, CD22, CD11c, CD25, CD103, and FMC7. Annexin A1, detected by immunohistochemistry, is highly specific for classic hairy cell leukemia and helps separate it from look-alikes including SBLPN (HCL variant) [1,2]. Furthermore, mandatory diagnostic evaluation now includes molecular testing for the BRAF V600E mutation as a standard of care, alongside Next-Generation Sequencing (NGS) to assess TP53 mutational status, MAP2K1 mutations, and IGHV gene rearrangements (specifically IGHV4-34), which carry significant prognostic implications for treatment response [8,10,11].
Other useful tests
- Liver function tests if hepatomegaly is present.
- Coagulation studies, because thrombocytopenia raises bleeding risk.
- BRAF V600E mutation testing, which confirms the diagnosis in classic hairy cell leukemia and guides targeted therapy decisions [3].
- Baseline abdominal imaging (Ultrasound or CT scan) to accurately evaluate deep intra-abdominal lymphadenopathy and measure baseline organomegaly [10,11].
Differential Diagnosis
Hairy cell leukemia shares features with several other blood disorders, so distinguishing it matters. The pattern of cytopenias, the immunophenotype, BRAF status, and bone marrow morphology together usually settle the question.
Lymphomas and other B-cell malignancies
- Splenic marginal zone lymphoma: Can mimic hairy cell leukemia with splenomegaly and cytopenias, but lacks the classic hairy cell morphology and Annexin A1 positivity.
- Chronic lymphocytic leukemia (CLL): Usually shows lymphocytosis and a different immunophenotype (CD5+, CD23+, dim CD20).
- Mantle cell lymphoma and follicular lymphoma: Present with lymphadenopathy and distinct immunophenotypes.
- Splenic B-cell lymphoma/leukemia with prominent nucleoli (SBLPN): Previously called HCL variant — covered below.
Myeloid and other conditions
- Primary myelofibrosis: Shares marrow fibrosis and splenomegaly but lacks hairy cells and the HCL immunophenotype.
- Chronic myelogenous leukemia (CML): Shows leukocytosis and the Philadelphia chromosome.
- Aplastic anemia: Pancytopenia without malignant cells.
- Myelodysplastic syndromes: Ineffective hematopoiesis and dysplastic features.
Treatment and Management
Treatment has been transformed over the last few decades. The goal today is durable remission with minimal toxicity, and most patients achieve it.
Watch and wait: not everyone needs treatment immediately
A key principle: treatment is offered only when hairy cell leukemia becomes symptomatic [1,2]. Standard criteria for starting treatment include:
- Hemoglobin below 11 g/dL
- Platelets below 100 × 10⁹/L
- Absolute neutrophil count below 1.0 × 10⁹/L
- Symptomatic splenomegaly
- Constitutional symptoms (fevers, weight loss, night sweats) or recurrent infections
Patients who don't meet these criteria are watched with regular blood counts and clinical review. This "watch and wait" approach can feel counterintuitive as it often raises real anxiety for patients and families, but it spares people unnecessary chemotherapy when the disease is quiet.
First-line therapy
The cornerstone of first-line treatment remains purine analogs, specifically cladribine or pentostatin. However, modern guidelines strongly favor upfront combination chemoimmunotherapy by combining cladribine with rituximab (either concurrently or sequentially) rather than monotherapy [2,8,9,11].
Concurrent cladribine and rituximab (CDA-R) achieves minimal residual disease (MRD)–negative complete remission rates exceeding 95%, significantly prolonging progression-free survival and reducing relapse rates compared to purine analog monotherapy. In patients with active uncontrolled infection, purine analogs should be deferred, and initial control of the disease can be safely achieved using non-myelosuppressive BRAF inhibitor monotherapy or interferon [8,10,11].
Treatment of relapsed or refractory disease
Management of relapsed disease is dictated by the duration of the initial response [8,10,11]:
- Late Relapse (> 2 Years): Patients who enjoy a remission lasting longer than two years after initial purine analog therapy can be successfully retreated with a purine analog combined with rituximab.
- Early Relapse (≤ 2 Years) or Refractory Disease: For patients relapsing within 24 months or those refractory to purine analogs, targeted therapy avoids cumulative bone marrow toxicity. Recommended regimens include [2,7,8,10]:
- BRAF Inhibitors + Anti-CD20: Vemurafenib combined with rituximab, or dabrafenib plus the MEK inhibitor trametinib [7,8,11].
- Novel Targeted Agents: BTK inhibitors (e.g., ibrutinib or zanubrutinib) or the BCL-2 inhibitor venetoclax (with or without rituximab) [2,10].
- Immunotoxins & Chemoimmunotherapy: Re-treatment regimens such as bendamustine plus rituximab [2,10].
Response Evaluation and MRD Monitoring
Response assessment following cladribine therapy should be intentionally delayed until 3 to 4 months post-treatment (and up to 6 months following pentostatin) [8,11]. This delayed timeframe allows full clearance of apoptotic leukemic cells and complete recovery of normal bone marrow hematopoiesis.
Minimal Residual Disease (MRD) monitoring in peripheral blood and bone marrow aspirates via highly sensitive flow cytometry or molecular assays (PCR/NGS) is now standard practice to assess depth of response and guide potential consolidation strategies [8,9,11].
Splenectomy
Once a cornerstone, splenectomy is now rare. It is reserved for selected patients with symptomatic splenomegaly that doesn't respond to medical therapy.
Supportive care
Given the profound immune suppression caused by both the underlying monocytopenia and purine analog therapy, rigorous supportive care is essential [2,8,11]:
- Anti-infective Prophylaxis: Mandatory administration of antimicrobial prophylaxis during and following purine analog therapy including Pneumocystis jirovecii pneumonia (PJP) prophylaxis (e.g., trimethoprim-sulfamethoxazole) and antiviral coverage (e.g., acyclovir or valacyclovir) until CD4+ T-lymphocyte counts recover (> 200 cells/µL) [8,11].
- Vaccinations: Pre-treatment administration of non-live vaccines, including seasonal influenza, COVID-19, pneumococcal, and recombinant zoster vaccines. Live vaccines are strictly contraindicated during and following immunosuppressive therapy [8,10,11].
- Transfusion Protocols: Irradiation of all cellular blood components (packed red blood cells and platelets) is required following purine analog treatment to prevent Transfusion-Associated Graft-versus-Host Disease (TA-GVHD) [8,11].
- Growth Factors: Granulocyte colony-stimulating factor (G-CSF) for severe neutropenia complicated by active infection [1,2].
Monitoring
Patients are followed long-term with periodic CBCs, liver function tests, clinical assessment of spleen size, and bone marrow biopsy when needed to confirm remission depth.
Prognosis
The outlook for hairy cell leukemia is one of the success stories of modern hematology. Most patients live for many years with good quality of life [2,4].
- 5-year overall survival: approximately 95%.
- 10-year overall survival: approximately 87%.
Long-term Italian follow-up of cladribine-treated patients shows survival approaching that of the matched general population [4]. Key factors that influence outcomes include age and overall health, depth of response to first-line therapy, and how well infections are controlled during treatment.
Hairy Cell Leukemia Variant: SBPLN
What used to be called "hairy cell leukemia variant" has been formally reclassified by the World Health Organization in 2022 as Splenic B-cell Lymphoma/Leukemia with Prominent Nucleoli (SBLPN) [5]. The change reflects a biological reality: this disease is not really a variant of classic hairy cell leukemia at all. It behaves differently, looks slightly different under the microscope, and responds poorly to the purine analogs that work so well in classic disease.
Key Differences
| Feature | Classic HCL | SBLPN (formerly HCL-V) |
|---|---|---|
| Driving mutation | BRAF V600E (nearly all cases) | No BRAF V600E; MAP2K1 mutations in some |
| Blood count | Pancytopenia, monocytopenia | Often lymphocytosis; normal monocytes |
| Cell morphology | Small lymphocytes with hairy projections | Medium–large cells with prominent nucleoli |
| Immunophenotype | CD25+, Annexin A1+ | CD25 usually negative, Annexin A1 negative |
| Bone marrow | Dry tap, fibrosis common | Usually aspirable |
| Spleen | Enlarged | Enlarged |
| First-line treatment | Cladribine ± rituximab | Cladribine + rituximab, or rituximab-based chemotherapy |
| Median survival | Approaches normal life span | About 7–9 years |
Recognizing SBLPN matters because the treatment differs and the prognosis is more guarded [1,5].
Frequently Asked Questions (FAQs)
What is hairy cell leukemia, in simple terms?
Hairy cell leukemia is a rare, slow-growing blood cancer in which the body makes too many of a particular kind of mature B lymphocyte. Under the microscope these cells look "hairy" because of fine projections on their surface. They build up in the bone marrow and spleen and crowd out normal blood cell production, leading to fatigue, infections, and easy bruising.
How is hairy cell leukemia diagnosed?
Diagnosis combines a few tests: a complete blood count usually shows low numbers across red cells, white cells, and platelets (pancytopenia), often with very low monocytes; a blood smear may reveal the characteristic hairy cells; a bone marrow biopsy confirms infiltration; and flow cytometry plus immunohistochemistry (including Annexin A1) identify the typical surface markers. BRAF V600E mutation testing supports the diagnosis in classic hairy cell leukemia.
Does every patient with hairy cell leukemia need treatment right away?
No. Many patients are watched without treatment if they have no symptoms and their blood counts are not dangerously low. Treatment usually starts when hemoglobin drops below 11 g/dL, platelets below 100 × 10⁹/L, neutrophils below 1.0 × 10⁹/L, or the spleen becomes uncomfortably enlarged. This "watch and wait" approach is standard for slow-growing blood cancers.
What is the first-line treatment for hairy cell leukemia today?
The standard first-line treatment is a purine analog, either cladribine or pentostatin. Increasingly, hematologists add rituximab to the purine analog to produce deeper, longer-lasting remissions. BRAF inhibitors (like vemurafenib) and BTK inhibitors are mainly used when the disease comes back or doesn't respond to first-line therapy.
What is the outlook for someone diagnosed with hairy cell leukemia?
The outlook is excellent for most patients. More than 95% are alive at 5 years, and many achieve long remissions that approach a normal life span. The disease is not usually considered curable, but it is highly controllable, and relapses can often be treated successfully with the same or a different drug.
Is hairy cell leukemia the same as "hairy cell leukemia variant"?
No. HCL variant is biologically different from classic hairy cell leukemia. It lacks the BRAF V600E mutation, doesn't show low monocytes, and responds less well to standard purine analogs. In 2022, the World Health Organization renamed it Splenic B-cell Lymphoma/Leukemia with Prominent Nucleoli (SBLPN) to reflect that it is a separate disease. Treatment usually involves rituximab combined with chemotherapy.
Glossary of Related Medical Terms
- B lymphocyte (B cell): A type of white blood cell that produces antibodies to fight infection. HCL is a cancer of mature B cells.
- BRAF V600E mutation: A specific change in the BRAF gene that switches on a growth-signaling pathway and drives nearly all cases of classic HCL.
- Pancytopenia: A drop in all three main blood cell types — red cells, white cells, and platelets — at the same time.
- Monocytopenia: A low monocyte count. Monocytes are infection-fighting white cells. Their drop is a hallmark of HCL.
- Splenomegaly: An enlarged spleen, often felt below the left rib cage.
- Hepatomegaly: An enlarged liver.
- Bone marrow biopsy: A small sample of bone marrow tissue taken (usually from the back of the hip) to look at how blood cells are made.
- "Dry tap": When the doctor cannot aspirate liquid marrow because scarring (fibrosis) makes it solid. Common in HCL.
- Flow cytometry: A lab test that uses lasers and antibodies to identify the proteins on cell surfaces, helping classify the type of leukemia.
- Immunophenotype: The pattern of surface proteins on a cell. In HCL, hairy cells typically show CD19, CD20, CD22, CD11c, CD25, CD103, and FMC7.
- Annexin A1: A protein that is highly specific to hairy cells and used to confirm the diagnosis on biopsy.
- Purine analogs: A class of chemotherapy drugs (cladribine and pentostatin) that look like the building blocks of DNA. They are the first-line treatment for HCL.
- Rituximab: A monoclonal antibody that targets CD20 on B cells. Increasingly combined with cladribine in HCL.
- BRAF inhibitor: A targeted drug (e.g., vemurafenib) that blocks the mutated BRAF protein driving HCL.
- Minimal residual disease (MRD): Tiny amounts of leukemia cells left after treatment that are not visible on a routine smear but can be picked up by sensitive tests.
- Remission: A state where signs and symptoms of leukemia have decreased or disappeared.
Disclaimer: This article is intended for educational and informational purposes only. It is not intended to be a substitute for informed professional medical advice, diagnosis, or treatment. While the information presented here is derived from credible medical sources and is believed to be accurate and up-to-date, it is not guaranteed to be complete or error-free. See additional information.
References
- Falini, B., & Tiacci, E. (2024). Hairy-Cell Leukemia. The New England journal of medicine, 391(14), 1328–1341. https://doi.org/10.1056/NEJMra2406376
- Troussard, X., Maître, E., & Paillassa, J. (2024). Hairy cell leukemia 2024: Update on diagnosis, risk-stratification, and treatment-Annual updates in hematological malignancies. American journal of hematology, 99(4), 679–696. https://doi.org/10.1002/ajh.27240
- Tiacci, E., Trifonov, V., Schiavoni, G., Holmes, A., Kern, W., Martelli, M. P., Pucciarini, A., Bigerna, B., Pacini, R., Wells, V. A., Sportoletti, P., Pettirossi, V., Mannucci, R., Elliott, O., Liso, A., Ambrosetti, A., Pulsoni, A., Forconi, F., Trentin, L., Semenzato, G., … Falini, B. (2011). BRAF mutations in hairy-cell leukemia. The New England journal of medicine, 364(24), 2305–2315. https://doi.org/10.1056/NEJMoa1014209
- Pagano, L., Criscuolo, M., Broccoli, A., Piciocchi, A., Varettoni, M., Galli, E., Anastasia, A., Cantonetti, M., Trentin, L., Kovalchuk, S., Orsucci, L., Frustaci, A., Spolzino, A., Volpetti, S., Annibali, O., Storti, S., Stelitano, C., Marchesi, F., Offidani, M., Casadei, B., … Zinzani, P. L. (2022). Long-term follow-up of cladribine treatment in hairy cell leukemia: 30-year experience in a multicentric Italian study. Blood cancer journal, 12(7), 109. https://doi.org/10.1038/s41408-022-00702-9
- Alaggio, R., Amador, C., Anagnostopoulos, I., Attygalle, A. D., Araujo, I. B. O., Berti, E., Bhagat, G., Borges, A. M., Boyer, D., Calaminici, M., Chadburn, A., Chan, J. K. C., Cheuk, W., Chng, W. J., Choi, J. K., Chuang, S. S., Coupland, S. E., Czader, M., Dave, S. S., de Jong, D., … Xiao, W. (2022). The 5th edition of the World Health Organization Classification of Haematolymphoid Tumours: Lymphoid Neoplasms. Leukemia, 36(7), 1720–1748. https://doi.org/10.1038/s41375-022-01620-2
- Bouroncle, B. A., Wiseman, B. K., & Doan, C. A. (1958). Leukemic reticuloendotheliosis. Blood, 13(7), 609–630. https://doi.org/10.1182/blood.V13.7.609.609
- Tiacci, E., De Carolis, L., Simonetti, E., Capponi, M., Ambrosetti, A., Lucia, E., Antolino, A., Pulsoni, A., Ferrari, S., Zinzani, P. L., Ascani, S., Perriello, V. M., Rigacci, L., Gaidano, G., Della Seta, R., Frattarelli, N., Falcucci, P., Foà, R., Visani, G., Zaja, F., … Falini, B. (2021). Vemurafenib plus Rituximab in Refractory or Relapsed Hairy-Cell Leukemia. The New England journal of medicine, 384(19), 1810–1823. https://doi.org/10.1056/NEJMoa2031298
- Zent, C. S., Tiacci, E., Kreitman, R. J., Tadmor, T., Tallman, M. S., Wörmann, B., Andritsos, L. A., Arons, E., Banerji, V., Barrientos, J. C., Bhat, S. A., Blachly, J. S., Broccoli, A., Call, T. G., Dearden, C., Demeter, J., Dietrich, S., El-Sharkawi, D., Fagarasanu, A., Falini, B., … Grever, M. R. (2026). Updated consensus guidelines for the diagnosis and management of patients with HCL and HCL variant. Blood, 148(1), 31–42. https://doi.org/10.1182/blood.2025032757
- Chihara, D., Arons, E., Stetler-Stevenson, M., Yuan, C. M., Wang, H. W., Zhou, H., Raffeld, M., Xi, L., Steinberg, S. M., Feurtado, J., James, L., Wilson, W., Braylan, R. C., Calvo, K. R., Maric, I., Dulau-Florea, A., & Kreitman, R. J. (2020). Randomized Phase II Study of First-Line Cladribine With Concurrent or Delayed Rituximab in Patients With Hairy Cell Leukemia. Journal of clinical oncology : official journal of the American Society of Clinical Oncology, 38(14), 1527–1538. https://doi.org/10.1200/JCO.19.02250
- National Comprehensive Cancer Network (NCCN). (2026). NCCN Clinical Practice Guidelines in Oncology: Hairy Cell Leukemia (Version 2.2027).
- Grever, M. R., Abdel-Wahab, O., Andritsos, L. A., Banerji, V., Barrientos, J., Blachly, J. S., Call, T. G., Catovsky, D., Dearden, C., Demeter, J., Else, M., Forconi, F., Gozzetti, A., Ho, A. D., Johnston, J. B., Jones, J., Juliusson, G., Kraut, E., Kreitman, R. J., Larratt, L., … Falini, B. (2017). Consensus guidelines for the diagnosis and management of patients with classic hairy cell leukemia. Blood, 129(5), 553–560. https://doi.org/10.1182/blood-2016-01-689422