Key Takeaways
Folate deficiency is a lack of vitamin B9, a nutrient the body needs to make DNA, divide cells, and produce healthy red blood cells [1].
- Symptoms ▾: The classic clinical picture is a megaloblastic anemia with fatigue, pale skin, glossitis (a sore inflamed tongue), and sometimes low platelets and white cells.
- Laboratory Investigations ▾: Folate deficiency is diagnosed by serum folate (deficient if <3 ng/mL), a full blood count showing a raised MCV, and a peripheral smear showing large red cells and hypersegmented neutrophils [6].
- Treatment ▾: Treatment is oral folic acid 1 to 5 mg daily until the anemia resolves, plus correction of the underlying cause; vitamin B12 must be checked and replaced first to avoid masking B12 deficiency [6].
*Click ▾ for more information
Introduction
Folate deficiency is one of the most common nutritional anemias worldwide, and one of the most clinically important. It is also one of the easiest to miss, because the early symptoms are vague and the treatment is cheap. This guide walks through what folate does, why it runs short, how to recognize it, and how it is treated using current evidence and guidelines.
Folate vs. Folic Acid: Understanding the Difference
Folate is the natural form of vitamin B9, found in leafy greens, legumes, citrus fruit, and liver.
Folic acid is the synthetic form used in supplements and food fortification. Folic acid is actually absorbed more efficiently than dietary folate (close to 100% bioavailability compared with roughly 50%), but it must be converted to its active form, tetrahydrofolate, by the enzyme dihydrofolate reductase (DHFR) in the intestine and liver [7]. This conversion is the same step blocked by drugs like methotrexate and trimethoprim, which is why these medications can produce folate deficiency.
Pathogenesis
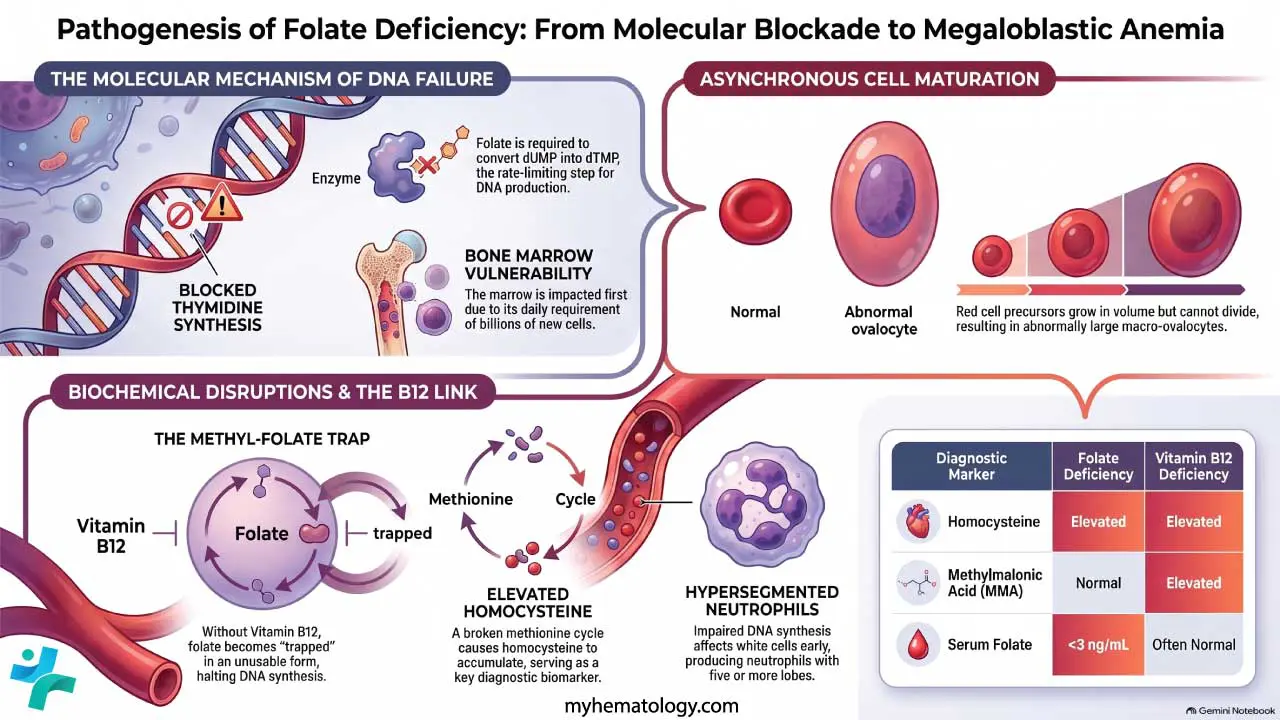
Folate's central job is to carry one-carbon units around the cell. Two of those reactions are essential to understand.
DNA synthesis. Folate, in the form of 5,10-methylenetetrahydrofolate, donates a methyl group to make thymidine (dTMP) from uridine (dUMP), in a reaction catalyzed by thymidylate synthase. Without enough folate, cells cannot make new DNA strands fast enough to keep up with cell division. Bone marrow is hit first because it produces billions of cells a day. Red cell precursors keep growing in size while waiting for DNA to be ready, which is why mature red cells end up abnormally large. This is the mechanism behind megaloblastic anemia [1].
Methylation reactions. Folate also feeds into the methionine cycle, which produces S-adenosylmethionine, the body's main methyl donor. Disruption here raises homocysteine, a useful diagnostic clue.
Methyl-folate trap
In vitamin B12 deficiency, folate gets stuck as methyltetrahydrofolate and cannot be recycled for DNA synthesis. The patient effectively becomes folate-deficient even with normal folate intake. This explains why B12 deficiency produces the same megaloblastic anemia as folate deficiency [5].
Causes of Folate Deficiency
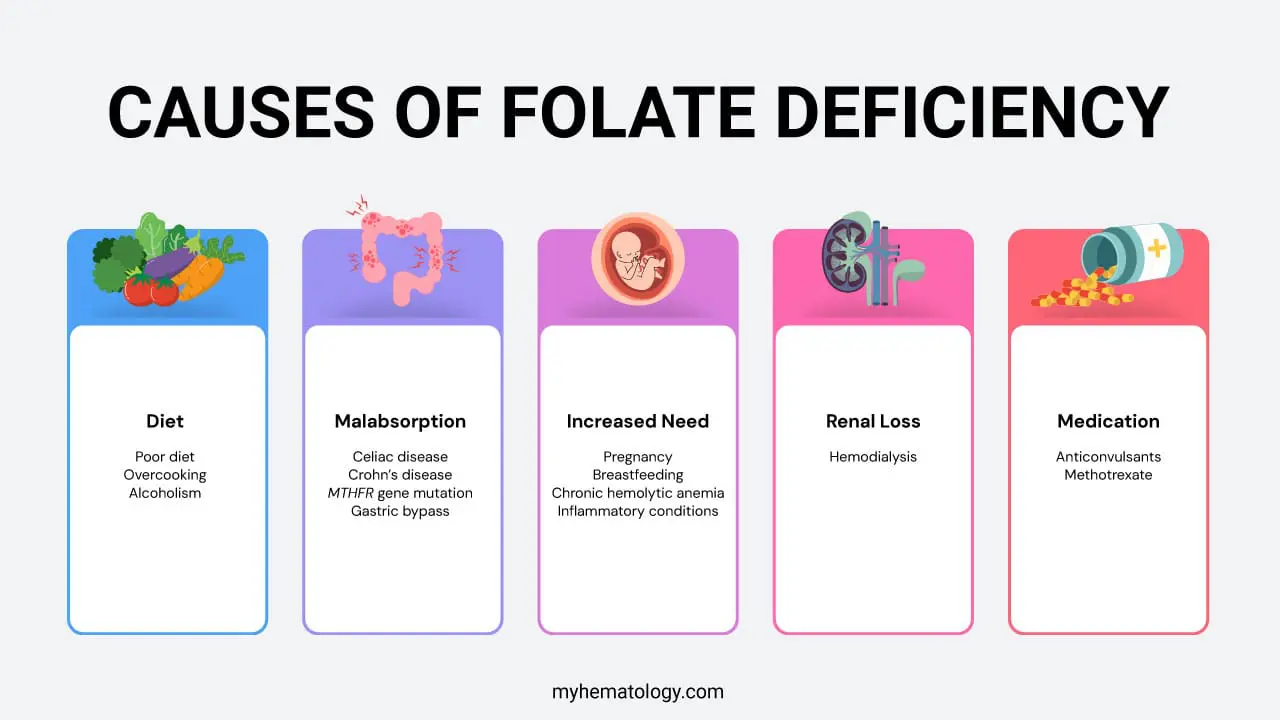
Folate stores last only about three to four months, so deficiency develops faster than B12 deficiency. Causes group into four buckets.
Inadequate intake. Diets low in vegetables, fruit, and legumes are the leading cause worldwide. Folate is also heat-sensitive, so prolonged cooking destroys it.
Malabsorption. Celiac disease, tropical sprue, inflammatory bowel disease, and chronic diarrhea reduce absorption in the upper small intestine. Bariatric surgery is an increasingly common cause and is worth flagging in any patient with unexplained macrocytosis after weight-loss surgery.
Increased demand. Pregnancy, lactation, hemolytic anemias (where the bone marrow works overtime), exfoliative skin disease, and rapid growth in infancy all raise the daily folate requirement.
Drugs and toxins. Several drugs are directly antifolate: methotrexate and trimethoprim inhibit DHFR; phenytoin, carbamazepine, valproate, and sulfasalazine lower folate by less direct mechanisms. Chronic alcohol use reduces both intake and absorption and is one of the classic causes in older adult medicine. While standard folic acid is often used prophylactically for patients on low-dose methotrexate, acute methotrexate toxicity or profound DHFR inhibition requires treatment with folinic acid (leucovorin). Folinic acid is a fully reduced folate derivative that completely bypasses the DHFR enzyme blocked by methotrexate [10].
Folate Deficiency Symptoms and Signs
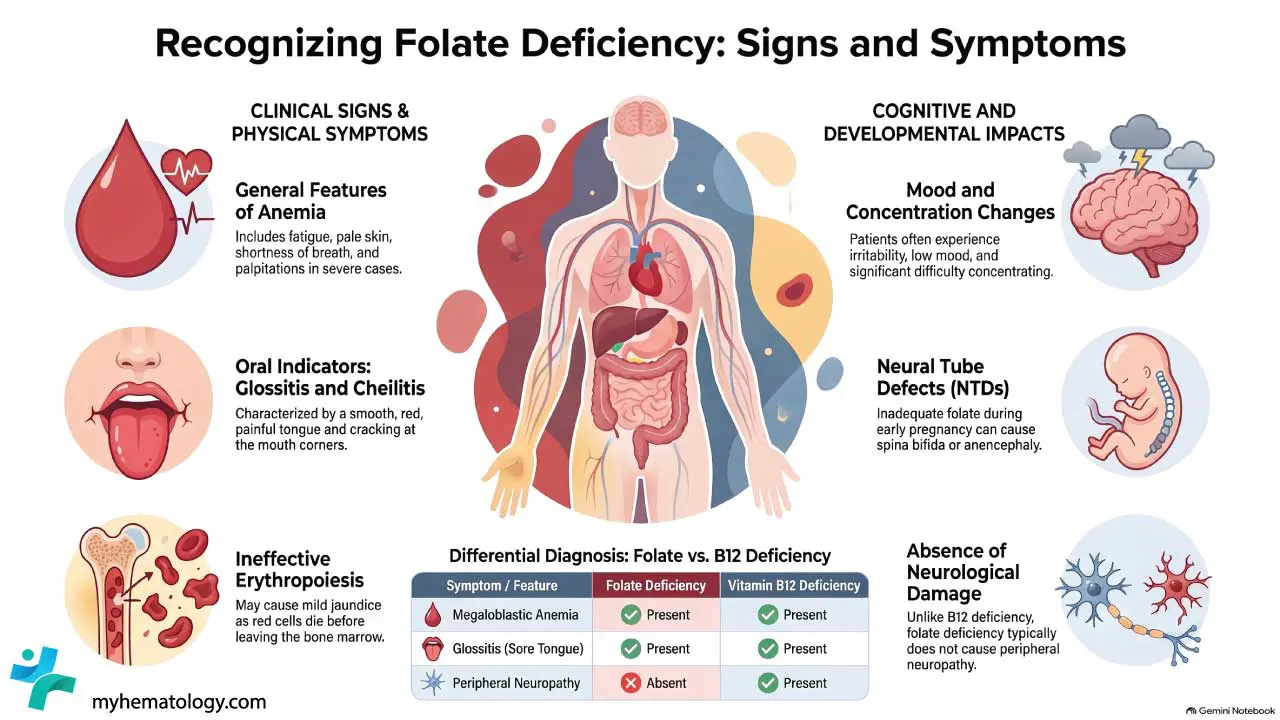
Symptoms scale with severity. Early deficiency may be silent or only show as fatigue. As anemia develops, more recognizable features appear.
General features of anemia
- Fatigue, weakness, reduced exercise tolerance
- Pale skin and conjunctivae
- Shortness of breath on exertion
- Palpitations and tachycardia in more severe anemia
Features that point toward folate (or B12) deficiency specifically
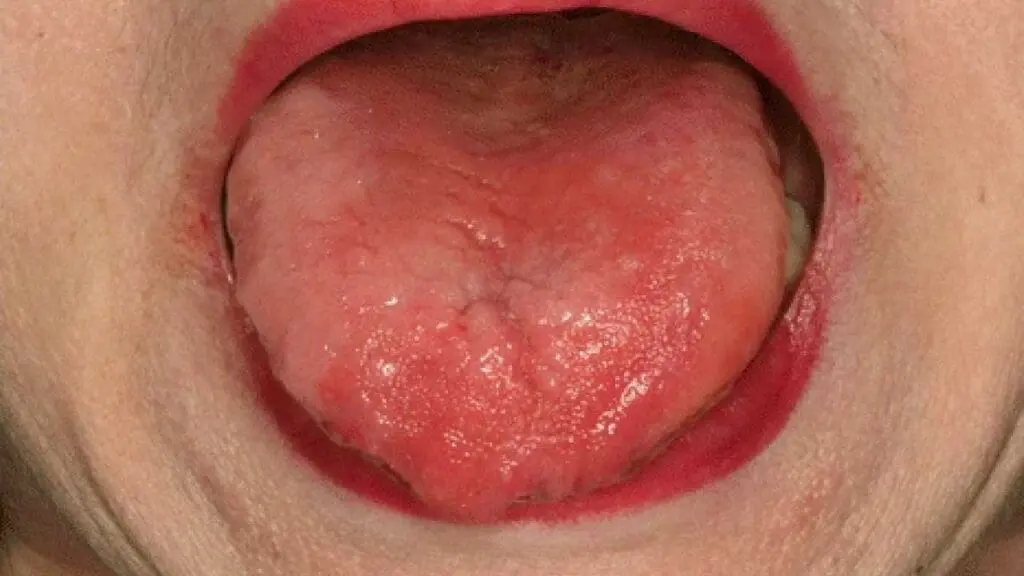
- Glossitis: A smooth, red, painful tongue from loss of papillae
- Angular cheilitis: Cracking at the corners of the mouth
- Mild jaundice from ineffective erythropoiesis (the bone marrow makes red cells that die before leaving the marrow)
- Mood changes: Irritability, low mood, difficulty concentrating
Unlike B12 deficiency, folate deficiency does not typically cause peripheral neuropathy or the spinal cord changes of subacute combined degeneration. If those features appear, think B12 first.
Folate and Pregnancy: Neural Tube Defects
Folate's role in early pregnancy is the reason every prenatal vitamin contains folic acid. The neural tube closes by day 28 after conception, often before pregnancy is recognized. Inadequate folate at this point can leave the tube open, producing spina bifida or, at the severe end, anencephaly [2,3].
The 2023 USPSTF guideline gives an A-grade recommendation for daily folic acid 400 to 800 mcg in anyone planning or capable of pregnancy, starting at least one month before conception and continuing through the first two to three months [2]. Women at higher risk (previous NTD pregnancy, valproate or carbamazepine use, pre-existing diabetes, or obesity) need a higher dose of 4 to 5 mg daily, prescribed rather than over the counter [6].
Laboratory Investigations
Lab workup serves two purposes: confirm folate deficiency, and rule out B12 deficiency before treatment.
Full Blood Count (FBC/CBC). Look for anemia (low hemoglobin) with a raised MCV (>100 fL), often in the 110–130 fL range. White cells and platelets may also be low in severe cases (pancytopenia).
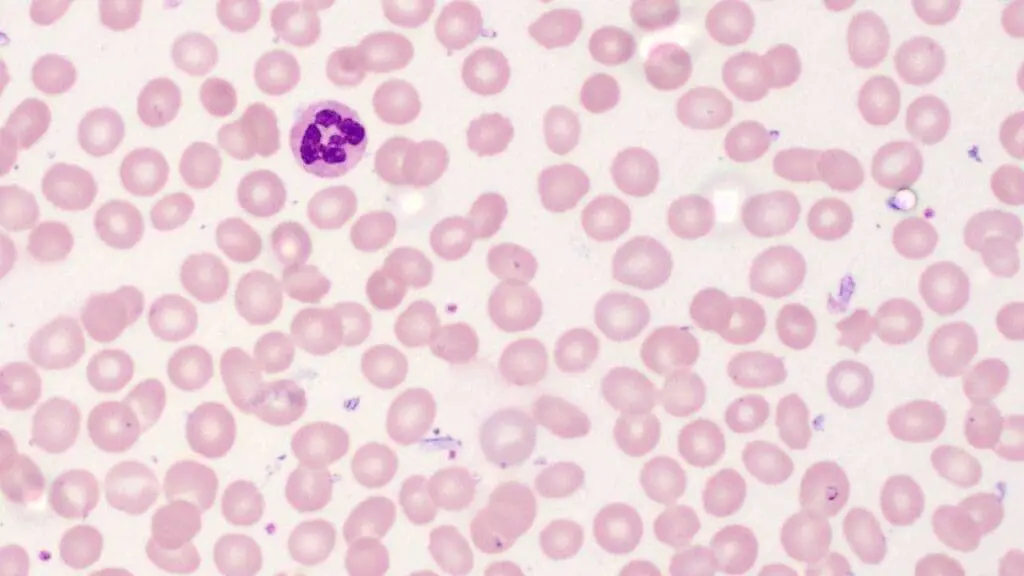
Peripheral blood smear. Two findings are classic:
- Large, oval red cells (macro-ovalocytes)
- Hypersegmented neutrophils (≥5 lobes) — often the earliest morphological clue, sometimes appearing before frank anemia
Serum folate. The standard first-line test. A level <3 ng/mL (7 nmol/L) confirms deficiency, while a level >5.9 ng/mL usually rules it out. Although fasting was traditionally recommended, non-fasting samples are now widely accepted for initial screening [6]. If the result falls in the indeterminate range (3–5.9 ng/mL), check homocysteine and methylmalonic acid (MMA); an elevated homocysteine with a normal MMA confirms tissue-level folate deficiency [8].
Red blood cell (RBC) folate. Major hematology guidelines, including the British Society for Haematology, now strongly recommend against routine RBC folate testing. The assay is costly, subject to high analytical variability, and rarely changes clinical management once serum folate and B12 are evaluated [6,11]. If metabolite testing (homocysteine/MMA) is unavailable for a borderline serum result, a therapeutic trial of folic acid (after verifying normal B12) is a clinically acceptable alternative.
Vitamin B12 level. Always check before treatment. If B12 is also low, replace B12 first or alongside folate.
Homocysteine and methylmalonic acid (MMA). Both rise in B12 deficiency; only homocysteine rises in folate deficiency. This pattern helps separate the two when levels are equivocal.
A peripheral smear in folate deficiency shows large, oval red cells and hypersegmented neutrophils. The picture is identical to B12 deficiency, which is why biochemical testing is essential.
Treatment and Management
Treatment has three parts: replace folate, treat the cause, and rule out B12 deficiency first.
Step 1: Check B12. This is the single most important rule. Giving folic acid alone to someone with undiagnosed B12 deficiency can correct the anemia but allow neurological damage to progress. Always check serum B12 before starting folate replacement [6].
Step 2: Replace folate. The standard adult treatment dose is 1 to 5 mg of oral folic acid daily (1 mg is standard in the US; 5 mg is the standard formulation in the UK and parts of Europe). Treatment must continue for a full four months. Because the lifespan of a red blood cell is approximately 120 days, a four-month course ensures that all folate-deficient megaloblastic red cells are completely replaced by healthy erythrocytes [9]. In cases of irreversible malabsorption, treatment may be lifelong [1,6]. Clinicians should also monitor for transient hypokalemia during the first week of treatment, as the rapid burst of new red blood cell production consumes serum potassium [9].
Step 3: Treat the cause. Dietary advice, treating celiac disease, switching antifolate drugs where possible, or addressing alcohol use makes the difference between a one-off correction and a long-term cure.
Monitoring response. Reticulocytes (young red cells) rise within 2 to 3 days and peak around day 5 to 8 of treatment. Hemoglobin should normalize within 8 weeks. If it doesn't, look again for B12 deficiency, ongoing malabsorption, or an alternative diagnosis like myelodysplastic syndrome.
MTHFR Variants
MTHFR polymorphisms (especially C677T) are common variants that modestly reduce the activity of one folate-processing enzyme. For most carriers, dietary folate and standard folic acid supplementation work well. Routine MTHFR testing is not recommended by major guidelines, and L-methylfolate is rarely needed in clinical practice [6].
Prevention of Folate Deficiency
Prevention happens at three levels: diet, fortification, and targeted supplementation.
Diet. Folate-rich foods include dark leafy greens (spinach, kale), legumes (lentils, chickpeas), citrus, asparagus, broccoli, avocado, eggs, and liver. Brief steaming preserves folate better than boiling.
Food fortification. The United States has mandated folic acid fortification of enriched cereal grain products since 1998, and NTD rates fell by roughly a third afterward. The UK adopted mandatory fortification of non-wholemeal wheat flour in 2021. This is one of the most successful public-health hematology interventions of the modern era.
Targeted supplementation:
- Anyone who could become pregnant: 400–800 mcg daily [2]
- Pregnancy: 400–600 mcg daily, ideally as part of a prenatal vitamin
- High-risk preconception (previous NTD, valproate, diabetes, obesity): 4–5 mg daily [6]
- Chronic hemolysis (e.g., sickle cell disease, thalassemia): 1 mg daily, lifelong
- Patients on methotrexate for rheumatologic disease: 5 mg weekly, on a non-methotrexate day
Frequently Asked Questions (FAQs)
What is folate deficiency in simple terms?
Folate deficiency means the body does not have enough vitamin B9 to make DNA and healthy red blood cells. The most common signs are fatigue, pale skin, a sore tongue, and a type of anemia called megaloblastic anemia, where red blood cells become large and immature. It is usually caused by poor diet, pregnancy, certain medications, or gut conditions that block absorption.
How is folate deficiency different from vitamin B12 deficiency?
Both vitamins are needed to make DNA, so both deficiencies produce a similar megaloblastic anemia with large red blood cells. The key difference is the nervous system: B12 deficiency causes numbness, balance problems, and memory loss, while folate deficiency usually does not damage nerves. Giving folic acid to someone with undiagnosed B12 deficiency can fix the anemia but allow nerve damage to progress, which is why clinicians check B12 levels before treating folate deficiency.
What blood tests confirm folate deficiency?
The main test is serum folate, with levels below 3 ng/mL indicating deficiency. Red blood cell folate is more accurate for long-term stores but is harder to obtain. A full blood count typically shows anemia with a raised MCV, and a blood film may show large red cells and hypersegmented neutrophils. Homocysteine is raised, while methylmalonic acid stays normal, which helps distinguish folate from B12 deficiency.
How much folic acid should pregnant women take?
All women who could become pregnant should take 400 to 800 micrograms of folic acid daily, starting at least one month before conception and continuing through the first two to three months of pregnancy. Women with a previous pregnancy affected by a neural tube defect, those on antiepileptic drugs like valproate, or those with diabetes or obesity usually need a higher dose of 4 to 5 milligrams daily under medical advice.
Can folate deficiency cause low platelets?
Yes. Folate is needed for cell division in the bone marrow, which produces platelets as well as red and white blood cells. Severe folate deficiency can lower the platelet count, a condition called thrombocytopenia, and may also lower white cells. The counts usually recover within days to weeks after starting folic acid replacement.
Which medications can cause folate deficiency?
Several drugs interfere with folate metabolism. Methotrexate and trimethoprim block the enzyme DHFR, which activates folic acid. Antiepileptic drugs like phenytoin, carbamazepine, and valproate reduce folate levels by mechanisms that are still being studied. Sulfasalazine and some older chemotherapy agents also interfere with folate. Patients on long-term therapy with these drugs often need supplementation.
Glossary of Related Medical Terms
- Folate (vitamin B9): Naturally occurring B vitamin in leafy greens, legumes, and citrus, essential for making DNA and red blood cells.
- Folic acid: Synthetic form of vitamin B9 used in supplements and fortified foods. Better absorbed than dietary folate but must be activated by the enzyme DHFR.
- Erythropoiesis: The production of red blood cells in the bone marrow.
- Megaloblastic anemia: A type of anemia in which red blood cell precursors in the bone marrow are abnormally large because DNA synthesis is impaired.
- Macrocytosis: Red blood cells that are larger than normal, shown by a raised mean corpuscular volume (MCV >100 fL).
- Mean corpuscular volume (MCV): The average size of a red blood cell, reported on a full blood count.
- Hypersegmented neutrophils: White blood cells with five or more nuclear lobes; a sensitive early sign of folate or B12 deficiency on a blood smear.
- Thymidylate synthase: The enzyme that converts dUMP to dTMP using a folate cofactor; the rate-limiting step linking folate to DNA synthesis.
- Methyl-folate trap: A state in B12 deficiency where folate gets stuck as methyltetrahydrofolate and cannot be used for DNA synthesis, producing a functional folate deficiency.
- Neural tube defect (NTD): A birth defect of the brain or spinal cord, including spina bifida and anencephaly, caused by failure of the neural tube to close in early pregnancy.
- Thrombocytopenia: A low platelet count, which raises the risk of bruising and bleeding.
- Glossitis: Inflammation of the tongue, which can become red, smooth, and sore.
- Peripheral neuropathy: Damage to peripheral nerves causing numbness, tingling, or burning, usually in the hands and feet.
- DHFR (dihydrofolate reductase): The enzyme that converts folic acid to its active form; it is the target of methotrexate and trimethoprim.
- MTHFR: Methylenetetrahydrofolate reductase; an enzyme with common gene variants (e.g., C677T) that can mildly reduce folate processing.
Disclaimer: This article is intended for educational and informational purposes only . It is not intended to be a substitute for informed professional medical advice, diagnosis, or treatment. While the information presented here is derived from credible medical sources and is believed to be accurate and up-to-date, it is not guaranteed to be complete or error-free. See additional information.
References
- Baddam S, Khan KM, Jialal I. Folic Acid Deficiency. [Updated 2025 Jun 25]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2025 Jan-. Available from: https://www.ncbi.nlm.nih.gov/sites/books/NBK535377/
- US Preventive Services Task Force. Folic Acid Supplementation to Prevent Neural Tube Defects: US Preventive Services Task Force Reaffirmation Recommendation Statement. JAMA. 2023;330(5):454–459. https://doi.org/10.1001/jama.2023.12876
- Viswanathan, M., Urrutia, R. P., Hudson, K. N., Middleton, J. C., & Kahwati, L. C. (2023). Folic Acid Supplementation to Prevent Neural Tube Defects: Updated Evidence Report and Systematic Review for the US Preventive Services Task Force. JAMA, 330(5), 460–466. https://doi.org/10.1001/jama.2023.9864
- World Health Organization. (2015). Serum and red blood cell folate concentrations for assessing folate status in populations. WHO.
- Green R. (2017). Vitamin B12 deficiency from the perspective of a practicing hematologist. Blood, 129(19), 2603–2611. https://doi.org/10.1182/blood-2016-10-569186
- Devalia, V., Hamilton, M. S., Molloy, A. M., & British Committee for Standards in Haematology (2014). Guidelines for the diagnosis and treatment of cobalamin and folate disorders. British journal of haematology, 166(4), 496–513. https://doi.org/10.1111/bjh.12959
- Bailey, L. B., Stover, P. J., McNulty, H., Fenech, M. F., Gregory, J. F., 3rd, Mills, J. L., Pfeiffer, C. M., Fazili, Z., Zhang, M., Ueland, P. M., Molloy, A. M., Caudill, M. A., Shane, B., Berry, R. J., Bailey, R. L., Hausman, D. B., Raghavan, R., & Raiten, D. J. (2015). Biomarkers of Nutrition for Development-Folate Review. The Journal of nutrition, 145(7), 1636S–1680S. https://doi.org/10.3945/jn.114.206599
- Clarke, R., Refsum, H., Birks, J., Evans, J. G., Johnston, C., Sherliker, P., Ueland, P. M., Schneede, J., McPartlin, J., Nexo, E., & Scott, J. M. (2003). Screening for vitamin B-12 and folate deficiency in older persons. The American journal of clinical nutrition, 77(5), 1241–1247. https://doi.org/10.1093/ajcn/77.5.1241
- Hoffbrand, A. V., Chowdary, P., Collins, G. P., & Loke, J. (2024). Hoffbrand's Essential Haematology (9th ed.). Wiley-Blackwell.
- Howard, S. C., McCormick, J., Pui, C. H., Buddington, R. K., & Harvey, R. D. (2016). Preventing and Managing Toxicities of High-Dose Methotrexate. The oncologist, 21(12), 1471–1482. https://doi.org/10.1634/theoncologist.2015-0164
- Tran K, Mierzwinski-Urban M, Mahood Q; Authors. Folate Testing in People With Suspected Folate Deficiency: CADTH Health Technology Review [Internet]. Ottawa (ON): Canadian Agency for Drugs and Technologies in Health; 2022 Mar. Available from: https://www.ncbi.nlm.nih.gov/books/NBK596669/