Key Takeaways
B12 deficiency is a lack of vitamin B12 (cobalamin) severe enough to disrupt DNA synthesis, red blood cell production, or nerve function. It causes megaloblastic anemia and, if untreated, lasting neurological damage [1,6].
- Causes ▾: The two main causes are insufficient intake (mainly strict plant-based diets) and malabsorption, with pernicious anemia being the most common non-dietary cause [6,7].
- Symptoms ▾: Typical clinical features include fatigue, pale skin, breathlessness, paresthesia (numbness or tingling), balance problems, glossitis, and cognitive changes. Subacute combined degeneration of the spinal cord (SACDC) is the classic severe neurological complication [6].
- Diagnosis ▾: Modern diagnosis (NICE NG239, 2024) starts with total serum B12 or active B12 (holotranscobalamin), with MMA or homocysteine used when results are unclear or when nitrous oxide misuse is suspected [1].
- Treatment ▾: Treatment is B12 replacement, usually with intramuscular hydroxocobalamin for malabsorption or neurological involvement, and high-dose oral cyanocobalamin for dietary causes or maintenance [1,2].
*Click ▾ for more information
Introduction
Vitamin B12, also called cobalamin, is a water-soluble vitamin built around a central cobalt atom. It is a cofactor in two reactions the body cannot do without: making DNA and keeping the myelin coating around nerves intact. Without enough of it, blood and nerves both suffer.
This is why B12 deficiency matters far beyond simple tiredness. It can cause a distinctive type of anemia where red blood cells are large and immature, and it can damage the spinal cord in ways that may not fully reverse with treatment [6]. The good news: when caught early, B12 deficiency is straightforward to treat. The challenge is recognizing it, because symptoms are often vague and the blood test can mislead.
Causes of B12 Deficiency
B12 deficiency develops for two broad reasons. Either not enough is coming in, or what comes in cannot be absorbed.
Insufficient dietary intake
Vitamin B12 is made by bacteria. Humans get it almost entirely from animal products, including meat, fish, poultry, eggs, and dairy. Strict vegans and long-term vegetarians who do not take supplements or eat fortified foods are at the highest dietary risk [6,7]. Infants exclusively breastfed by deficient mothers are also vulnerable and can present with developmental delay [1].

Malabsorption
Even when dietary intake is adequate, several conditions can stop B12 from being absorbed:
- Pernicious anemia. An autoimmune disease that destroys the stomach cells producing intrinsic factor, a protein B12 needs to be absorbed in the terminal ileum. It is the commonest non-dietary cause of B12 deficiency [6,7].
- Atrophic gastritis. Chronic inflammation thins the stomach lining, reducing both acid and intrinsic factor production.
- Terminal ileum disease or resection. Crohn's disease, celiac disease, and surgical removal of the ileum all reduce B12 absorption because the ileum is where absorption happens.
- Bariatric surgery. Roux-en-Y gastric bypass and similar procedures reshape the gut and reduce intrinsic factor exposure.
- Long-term medications. Metformin (used for type 2 diabetes) and proton pump inhibitors (such as omeprazole) can interfere with absorption over years of use.
- Nitrous oxide (N₂O) misuse. Recreational inhalation of "nos," "whippits," or "galaxy gas" inactivates B12 inside the body by oxidizing its cobalt atom. This produces a functional B12 deficiency where the serum B12 level may look normal but the vitamin is biologically useless [5]. This cause is increasingly common in young adults.
Other risk factors
Aging gradually lowers stomach acid, which reduces B12 release from food. Heavy alcohol use damages the stomach lining and worsens absorption. Older adults on long-term PPIs or metformin sit in a particularly high-risk group.
Pathophysiology of B12 Deficiency
This is where the biochemistry pays off, so it is worth following carefully.

B12 acts as a cofactor for methionine synthase, the enzyme that converts homocysteine to methionine. This reaction also recycles folate, releasing it from its inactive form (5-methyl-THF) so it can be reused for DNA building blocks.
When B12 is missing, the enzyme stalls. Folate gets stuck as 5-methyl-THF and cannot be released. This is the methylfolate trap. DNA synthesis grinds down, but cells keep growing in size. The result is megaloblastic anemia: red blood cells that are abnormally large (macrocytic) but immature and short-lived [6].
A second B12-dependent enzyme, methylmalonyl-CoA mutase, converts methylmalonyl-CoA to succinyl-CoA. When B12 is low, methylmalonic acid (MMA) builds up. This is why MMA is such a specific marker of B12 deficiency.
The Folate Trap in B12 Deficiency
Giving folate alone to a B12-deficient patient can correct the anemia but allows neurological damage to progress. Always check B12 status before treating macrocytic anemia with folate [6,7].
Symptoms and Signs
B12 deficiency can affect blood, nerves, mind, and mouth. Symptoms develop slowly, often over months, which is why diagnosis is frequently delayed [1].

Hematological features
Megaloblastic anemia causes the familiar anemia symptoms: fatigue, weakness, breathlessness on exertion, pale skin, and palpitations. Severe cases may show mild jaundice from ineffective red cell production breaking down in the bone marrow.
Peripheral neurological features
Damage to peripheral nerves typically starts as paresthesia (numbness and tingling) in the hands and feet, often in a "glove and stocking" pattern. Muscle weakness, reduced reflexes, and balance problems can follow.
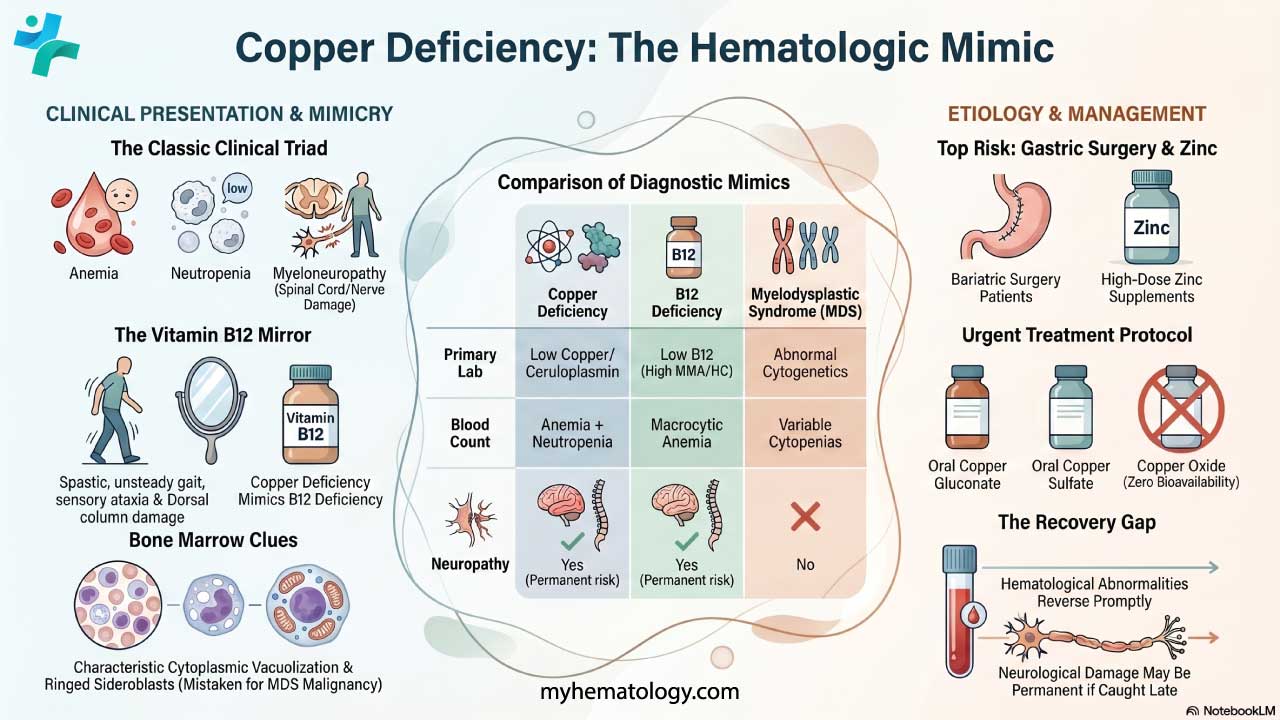
Subacute combined degeneration of the spinal cord (SACDC)
This is the classic and most serious neurological complication. B12 deficiency damages two specific tracts in the spinal cord [3,6]:
- Dorsal columns, which carry vibration and position sense. Loss produces a positive Romberg sign and an unsteady, wide-based gait.
- Lateral corticospinal tracts, which carry motor signals. Damage causes spasticity, hyperreflexia, and upgoing plantars (Babinski sign).
Patients describe a feeling of "walking on cotton wool." SACDC is a neurological emergency: prompt B12 replacement may partly reverse it, but delays leave permanent deficits.
Neuropsychiatric features
Memory loss, difficulty concentrating, low mood, irritability, and in advanced cases confusion or dementia-like presentations [8]. These often improve with treatment but can be misattributed to depression or early dementia.
Oral signs
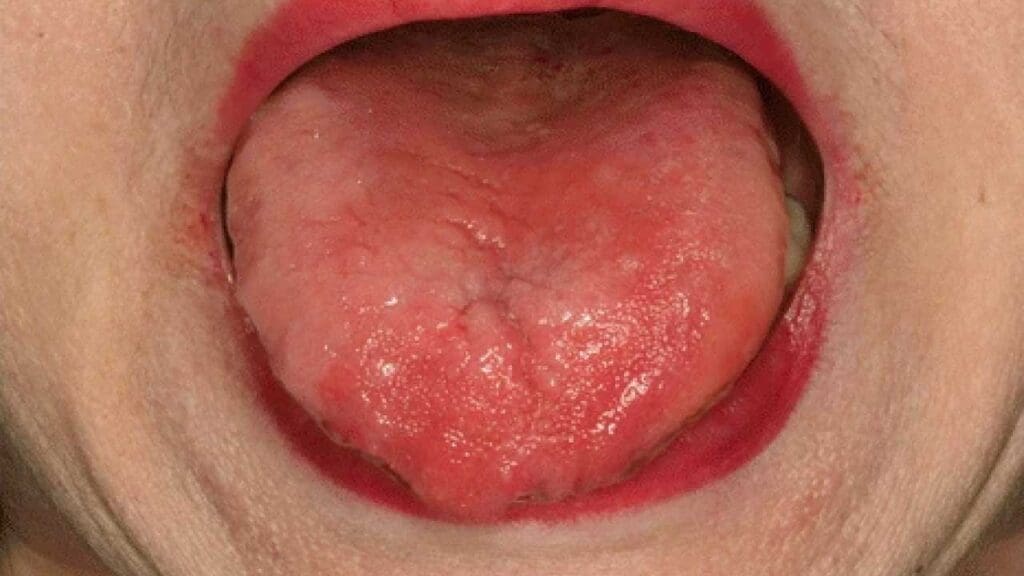
- Glossitis. A smooth, red, painful tongue caused by atrophy of the tongue papillae.
- Angular cheilitis. Painful cracking at the corners of the mouth.
Other features
Loss of appetite, weight loss, and occasional vision changes if the optic nerve is involved. Hair thinning can occur, though it is not a reliable specific sign.
Diagnosis of B12 Deficiency
Suspecting B12 deficiency starts with the history. The aim of testing is to confirm true deficiency, identify the cause, and rule out conditions that mimic it.
History and examination
Ask about diet, gastrointestinal surgery, autoimmune disease, long-term medications (metformin, PPIs), and recreational drug use, especially nitrous oxide. On examination, look for pallor, glossitis, neurological signs (vibration sense, proprioception, Romberg, gait, reflexes, plantar response), and signs of underlying disease.
How a Single Dose of B12 Obscures Diagnosis
Blood samples for B12, MMA, and intrinsic factor antibodies must be drawn before administering any B12 replacement. Even a single dose of B12 can normalize serum levels for months, rendering definitive diagnosis impossible [1]
First-line laboratory tests
A complete blood count (CBC) typically shows anemia with raised mean corpuscular volume (MCV > 100 fL), although the MCV can be normal if iron deficiency is also present. The blood film is highly informative: oval macrocytes, anisopoikilocytosis, and hypersegmented neutrophils (five or more nuclear lobes) are classic.
For B12 status itself, the 2024 NICE guideline (NG239) recommends starting with either total serum B12 or active B12 (holotranscobalamin) for most patients. However, active B12 is clinically mandated, not just preferred, during pregnancy or for patients on oral contraceptives, as total B12 naturally drops in these states causing false positives [1,4].
If nitrous oxide misuse is suspected, neither total nor active B12 are suitable first-line tests; clinicians must test methylmalonic acid (MMA) or plasma homocysteine first, as serum B12 levels often appear falsely normal in N₂O-induced functional deficiency [1,5].

Second-line tests
If the initial result is borderline or symptoms strongly suggest deficiency despite a normal level, measure [1,4]:
- Methylmalonic acid (MMA). Rises specifically in B12 deficiency.
- Homocysteine. Also rises, but elevation is non-specific and can occur in folate deficiency, renal impairment, and hypothyroidism.
Elevated MMA is particularly important when nitrous oxide misuse is suspected, because serum B12 may be normal in functional deficiency [5].
Investigating the cause
Once deficiency is confirmed, the next step is to identify why:
- Anti-intrinsic factor antibody. Highly specific for pernicious anemia. Sensitivity is only around 50%, so a negative result does not exclude the diagnosis.
- Upper GI endoscopy with biopsy. Considered if atrophic gastritis or gastric pathology is suspected.
The Schilling test is now historical. It used radioactive cobalamin to track absorption, but it is essentially unavailable today and has been replaced by the antibody and metabolite tests above [1].Early detection and treatment of B12 deficiency are crucial to prevent complications like permanent nerve damage. Vitamin B12 deficiency can sometimes be difficult to diagnose, especially in the early stages.
Vitamin B12 Deficiency Treatment
Treatment has three goals: replace the missing vitamin, treat the cause, and monitor recovery.
Choosing the form and route
Two main injectable forms exist:
- Hydroxocobalamin is preferred in the UK, Europe, and Australia because it binds more tightly to plasma proteins and lasts longer in tissues.
- Cyanocobalamin is more common in the United States.
For dietary deficiency, high-dose oral cyanocobalamin (typically 1,000–2,000 µg daily) is recommended. Additionally, recent guidelines support using high-dose oral replacement for medication-induced malabsorption (e.g., from long-term metformin or PPIs), as it relies on passive diffusion in the gut that bypasses the need for intrinsic factor [1,2]. Oral therapy is also recommended as an empiric trial for deficiency of uncertain cause, with clinical and hematological response reviewed at 3 months [1].
For severe or irreversible malabsorption, such as confirmed pernicious anemia, total gastrectomy, or complete terminal ileal resection, intramuscular hydroxocobalamin remains standard and mandatory. For these patients, lifelong IM injections must never be stopped or reduced, even if serum B12 normalizes or symptoms resolve [1].
For neurological involvement (including SACDC), the loading phase is more intensive: 1 mg IM on alternate days until no further improvement is seen, then 1 mg every 2 months [1,7].
For nitrous oxide-induced deficiency, stop the exposure and start parenteral B12 replacement promptly. Some clinicians add neuroprotective measures. Neurological recovery may take many months and is not always complete [5].
Treating the underlying cause
Patients with pernicious anemia need lifelong replacement. Vegans should switch to fortified foods or daily oral supplements. Patients on long-term metformin or PPIs may need periodic monitoring. Bariatric surgery patients typically need lifelong B12 supplementation.
Monitoring response
Reticulocyte count rises within a week of starting treatment, hemoglobin normalizes over 6 to 8 weeks, and the MCV settles by around 8 weeks. Neurological symptoms improve more slowly, over 3 to 12 months, and full recovery is not guaranteed if treatment is delayed [6]. Always re-check B12 and MMA after treatment is established, and reassess if symptoms return.event irreversible nerve damage and other complications. Even with treatment, some neurological damage might not be fully reversible.
Why Early Diagnosis Matters
B12 deficiency illustrates a recurring theme in hematology: a treatable nutritional disorder can cause permanent neurological harm if missed. The blood changes reverse easily. The spinal cord does not.
Frequently Asked Questions (FAQs)
What is B12 deficiency and why does it matter?
B12 deficiency means the body does not have enough vitamin B12 (cobalamin) to make healthy red blood cells, build DNA, or maintain the protective coating around nerves. Untreated, it can cause megaloblastic anemia and irreversible nerve damage, including damage to the spinal cord. Early diagnosis prevents permanent harm.
How is B12 deficiency diagnosed?
Current UK NICE guidance recommends either total serum B12 or active B12 (holotranscobalamin) as the first test. If results are borderline or unclear, doctors measure methylmalonic acid (MMA) or homocysteine, both of which rise when B12 is functionally deficient. A complete blood count and blood film typically show large red blood cells (macrocytosis) and hypersegmented neutrophils.
Can you have B12 deficiency with a normal B12 blood level?
Yes. This is called functional B12 deficiency. It is most often seen in people who use nitrous oxide recreationally, where the gas inactivates B12 inside the body. Serum B12 can look normal, but MMA and homocysteine are elevated and neurological symptoms can be severe.
Why are vegans at higher risk?
Vitamin B12 is made by bacteria and is found almost exclusively in animal-based foods such as meat, fish, eggs, and dairy. People following strict plant-based diets without fortified foods or supplements may not get enough B12 to meet daily needs. Risk increases over months to years because the liver stores B12 for a long time before symptoms emerge.
What is the treatment for B12 deficiency?
Treatment depends on the cause. For dietary deficiency, oral B12 supplements or fortified foods are usually enough. For malabsorption (such as pernicious anemia), intramuscular injections of hydroxocobalamin are standard, with a loading phase followed by maintenance doses every 2 to 3 months. If neurological symptoms are present, injections are given more frequently until symptoms stop improving.
Is the nerve damage from B12 deficiency reversible?
Partly. Hematological changes (anemia, abnormal blood cells) usually resolve within weeks of starting treatment. Neurological symptoms can improve over 3 to 12 months, but some damage may be permanent, especially if treatment is delayed. This is why early diagnosis matters.
Glossary of Related Medical Terms
- Cobalamin — The chemical name for vitamin B12. Contains a cobalt atom at its center.
- Intrinsic factor — A protein made by stomach cells that binds B12 so it can be absorbed in the terminal ileum.
- Pernicious anemia — An autoimmune disease that destroys the stomach cells that make intrinsic factor, blocking B12 absorption.
- Megaloblastic anemia — A type of anemia where red blood cells are abnormally large and immature because DNA synthesis is impaired.
- Macrocytosis — Red blood cells that are larger than normal, measured by MCV.
- Hypersegmented neutrophil — A white blood cell with five or more nuclear lobes; a classic blood film clue to B12 or folate deficiency.
- Methylmalonic acid (MMA) — A metabolite that builds up when B12 is functionally deficient. A more specific marker than serum B12.
- Homocysteine — An amino acid that rises in both B12 and folate deficiency. Less specific than MMA.
- Holotranscobalamin (active B12) — The fraction of B12 bound to transcobalamin and actually available to cells. Now an accepted first-line test.
- Methylfolate trap — The biochemical bottleneck in B12 deficiency: folate gets stuck as 5-methyl-THF and cannot be recycled for DNA synthesis.
- Subacute combined degeneration (SACDC) — Degeneration of the dorsal columns and lateral corticospinal tracts of the spinal cord caused by B12 deficiency.
- Glossitis — Inflammation of the tongue, often appearing smooth, red, and sore.
- Angular cheilitis — Cracking and inflammation at the corners of the mouth.
- Hydroxocobalamin / cyanocobalamin — Two injectable forms of B12. Hydroxocobalamin is preferred in the UK and Europe; cyanocobalamin is more common in the US.
Disclaimer: This article is intended for educational and informational purposes only. It is not intended to be a substitute for informed professional medical advice, diagnosis, or treatment. While the information presented here is derived from credible medical sources and is believed to be accurate and up-to-date, it is not guaranteed to be complete or error-free. See additional information.
References
- National Institute for Health and Care Excellence. (2024). Vitamin B12 deficiency in over 16s: Diagnosis and management (NICE Guideline NG239). https://www.nice.org.uk/guidance/ng239
- Wang, H., Li, L., Qin, L. L., Song, Y., Vidal-Alaball, J., & Liu, T. H. (2018). Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency. The Cochrane database of systematic reviews, 3(3), CD004655. https://doi.org/10.1002/14651858.CD004655.pub3.
- Garg, R., Malhotra, H., & Kumar, N. (2016). Approach to a case of myeloneuropathy. Annals of Indian Academy of Neurology, 19(2), 183–187. https://doi.org/10.4103/0972-2327.182303
- Tufail, N., Kataria, M., Chaudhary, A. J., Dhillon, R. A., Asif Naveed, M., & Mohsin, S. (2024). Comparing Holotranscobalamin and Total Vitamin B12 in Diagnosing Vitamin B12 Deficiency in Megaloblastic Anemia Patients. Cureus, 16(10), e71278. https://doi.org/10.7759/cureus.71278
- Garakani, A., Jaffe, R. J., Savla, D., Welch, A. K., Protin, C. A., Bryson, E. O., & McDowell, D. M. (2016). Neurologic, psychiatric, and other medical manifestations of nitrous oxide abuse: A systematic review of the case literature. The American journal on addictions, 25(5), 358–369. https://doi.org/10.1111/ajad.12372
- Stabler S. P. (2013). Vitamin B12 deficiency. The New England journal of medicine, 368(21), 2041–2042. https://doi.org/10.1056/NEJMc1304350
- Devalia, V., Hamilton, M. S., Molloy, A. M., & British Committee for Standards in Haematology (2014). Guidelines for the diagnosis and treatment of cobalamin and folate disorders. British journal of haematology, 166(4), 496–513. https://doi.org/10.1111/bjh.12959
- Health Quality Ontario (2013). Vitamin B12 and cognitive function: an evidence-based analysis. Ontario health technology assessment series, 13(23), 1–45.